


Cautious Optimism, Clearly Bounded
Participants were not opposed to AI-assisted autism screening. They saw genuine value in earlier identification, faster access to services, and a clearer picture of developmental concerns. That optimism, however, came with explicit conditions.
The risks they named were specific and structural:
- EHR data gaps — Electronic health records reflect existing patterns of care access. Populations with less consistent healthcare contact produce thinner records, which can skew model outputs and compound existing inequities.
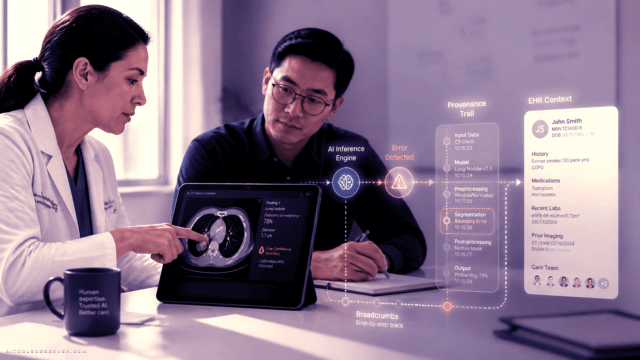
- Black-box opacity — When a model’s internal reasoning cannot be inspected or explained, clinicians and caregivers cannot meaningfully evaluate its outputs. Trust becomes difficult to establish without interpretability.
- Emotional burden on families — Very early screening can surface uncertainty before any actionable pathway exists, placing stress on families without a corresponding benefit.
- Caregiver exclusion — Tools that operate without caregiver input risk sidelining the people who know the child best and who must act on whatever the model suggests.
Each of these risks sits outside the scope of a standard performance benchmark.
The Timing Problem
One of the study’s more practically useful findings concerns timing. Participants did not simply want early screening — they wanted appropriately timed screening.
The distinction matters. Information about a child’s likelihood of autism was considered meaningful only when it was actionable: when families and clinicians could move directly from a result to a concrete next step. Screening that surfaces a probability score without a clear follow-up pathway was seen as generating anxiety rather than benefit.
This framing has direct implications for implementation design. A model that performs well in isolation may still cause harm if it is deployed at a point in the care pathway where no structured response is available.
What “Ethical Implementation” Actually Requires
The study’s authors argue that ethical deployment of clinical prediction models must be built into the implementation process, not treated as a compliance checkbox after the technical work is done.
Their specific recommendations point toward:
- Embedded ethical practices that address trust, equity, and caregiver-clinician partnership from the outset
- Active inclusion of interest-holders — caregivers, autistic adults, and providers — in shaping how tools are introduced and used
- Communication design that supports shared decision-making rather than delivering outputs in isolation
The autistic adults in the study are a notable inclusion. Their perspectives on how autism likelihood should be framed and communicated add a dimension that purely clinical or caregiver-focused research tends to miss.
Why This Matters for AI Tool Evaluation
For anyone evaluating clinical AI tools — whether as a health system administrator, a clinician, or a researcher — this study offers a useful reframe.
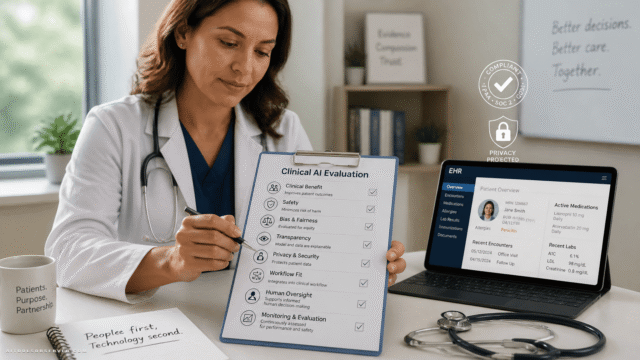
The questions worth asking before adoption are not only technical:
- Does the model perform equitably across populations with varying EHR completeness?
- Can its outputs be explained to a clinician or caregiver in plain terms?
- At what point in the care pathway does the tool intervene, and what happens next?
- Who was consulted in designing the communication of results?
These are not soft questions. They determine whether a tool that works in a controlled evaluation actually works in a clinical relationship.
A Practical Takeaway
The study is qualitative and draws on a small, specific sample. Its findings reflect the perspectives of these particular participants, not population-level outcome data. That is a real limitation — and the authors acknowledge it.
What the study does well is surface the gap between technical readiness and clinical readiness. An AI model can achieve strong predictive performance and still fail the people it is meant to serve if consent processes are unclear, if EHR bias goes unaddressed, or if families receive a probability score with no pathway forward.
For health systems considering adoption, the practical implication is straightforward: build the ethical infrastructure before the rollout, not after the complaints.






Comments (0) No comments yet
Want to join this discussion? Login or Register.
No comments yet. Be the first to share your thoughts!